Ai-O Publications
Publications by the Artificial Intelligence In Ophthalmology Center
Explicit Inclusion of Diabetes Mellitus Without Retinopathy within Diabetic Retinopathy Prediction

Authors: Rashidisabet, H., Lim, J.I., Kazlauskas, A., Yi, D.
Citation: Rashidisabet, H., Lim, J.I., Kazlauskas, A., Yi, D. “Revisiting Automated Diabetic Retinopathy Progression Prediction with Explicit Inclusion of Diabetes Mellitus Without Retinopathy.” Under review at Ophthalmology Science journal. [Corresponding author: Homa Rashidisabet]
Purpose: To evaluate whether explicitly modeling diabetes mellitus (DM) without Diabetic retinopathy (DR) as its own stage enables deep learning (DL) to detect early retinal changes for early risk identification of DR severity spectrum.
Conclusions: Explicitly modeling diabetes without retinopathy improved early-stage discrimination and revealed feature-reliance shifts with DR severity. Vessel- and saliency-based analyses identified subtle retinal changes preceding clinical DR.
Translational Relevance: Treating diabetes without retinopathy as its own stage may enhance early DR risk identification and aid development of clinically useful AI tools.
Improving Generalization of Deep Learning for Glaucoma Classification Under Clinical Domain Shift via Unsupervised Domain Adaptation

Authors: Rashidisabet, H., Chan, P., Vajaranant, T., Yi, D.
Citation: Rashidisabet, H., Chan, P., Vajaranant, T., Yi, D. “Generalizable Glaucoma Classification via Adversarial Domain Adaptation Under Clinical Domain Shifts.” Under second round of review at Ophthalmology Science journal.
Purpose: To develop and evaluate an unsupervised domain adaptation (UDA) framework for glaucoma classification from fundus images that improves the generalizability of deep learning (DL) models across heterogeneous imaging characteristics and clinical settings.
Conclusions: The proposed UDA framework improves cross-domain generalizability of DL-based glaucoma classification from fundus images. Compared with standard DL models, UDA exhibits feature utilization patterns more aligned with an ideal baseline, reducing over-reliance on optic nerve head-specific cues and supporting more robust decision-making under domain shift.
Translational Relevance: By enabling glaucoma classification without requiring labeled data from new clinical sites, this UDA framework addresses a key barrier to deploying AI-based screening tools across diverse real-world ophthalmic settings.
An Evaluation of the Mean Teacher Framework for Semi-Supervised Cataract Surgical Image Segmentation

Authors: Faraji, M., Yi, D., Heiferman, M.J., Rashidisabet, H.
Citation: Faraji, M., Yi, D., Heiferman, M.J., Rashidisabet, H. “Generalizable Multi-Disease Retinal Classification via Segmentation in a Small-Data Regime.” In preparation for Translational Vision Science & Technology journal. [Corresponding author: Homa Rashidisabet]
Purpose: To evaluate a semi-supervised Mean Teacher (MT) framework for semantic segmentation of cataract surgical images, addressing the challenge of limited labeled data in real-world clinical applications.
Conclusions: The MT framework provides an effective semi-supervised solution for surgical image segmentation with limited annotations. Full source code and utility scripts will be released upon acceptance at: https://github.com/mahtabfaraji1/Semi-supervised-segmentation-of-cataract-surgical-images.
Translational Relevance: Accurate segmentation of ocular anatomy and instruments supports surgical guidance, intraoperative decision-making, and training tools in data-limited clinical environments.
Robust Uncertainty-Informed Glaucoma Classification Under Data Shift

Authors: Rashidisabet, H., Chan, R.P., Leiderman, Y.I., Vajaranant, T.S. and Yi, D.
Purpose: Standard deep learning (DL) models often suffer significant performance degradation on out-of-distribution (OOD) data, where test data differs from training data, a common challenge in medical imaging due to real-world variations.
Conclusions: Our approach addresses the challenge of generalization in standard DL models for glaucoma classification across diverse datasets by selectively withholding predictions when the model is uncertain. This method reduces misclassification errors compared to state-of-the-art baselines, particularly for out-of-distribution cases.
Translational Relevance: This study introduces a tunable framework that explores the trade-off between prediction accuracy and data retention in glaucoma prediction. By managing uncertainty in model outputs, the approach lays a foundation for future decision support tools aimed at improving the reliability of automated glaucoma diagnosis.
Validating the Generalizability of Ophthalmic Artificial Intelligence Models on Real-World Clinical Data

Authors: Rashidisabet, H., Sethi, A., Jindarak, B., Edmonds, D., Chan, P., Leiderman, Y., Vajaranant, T., Yi, D.
Purpose. This study aims to investigate generalizability of deep learning (DL) models trained on commonly used public fundus images to an instance of Real-World Data (RWD) for glaucoma diagnosis.
Conclusions. DL models trained on commonly used public data have limited ability to generalize to RWD for classifying glaucoma. They perform similarly to RWD models for OD segmentation.
Translational Relevance: RWD is a potential solution for improving generalizability of DL models and enabling clinical translations in care of the prevalent blinding ophthalmic conditions, such as glaucoma.
Targeted Unlearning Using Perturbed Sign Gradient Methods With Applications On Medical Images

Authors: Nahass, G.R., Wang, Z., Rashidisabet, H., Kim, W.H., Hubschman, S., Peterson, J.C., Yazdanpanah, G., Purnell, C.A., Setabutr, P., Tran, A.Q. and Yi, D., Ravi, S.
Machine unlearning aims to remove the influence of specific training samples from a trained model without full retraining. While prior work has largely focused on privacy-motivated settings, we recast unlearning as a general-purpose tool for post-deployment model revision. Specifically, we focus on utilizing unlearning in clinical contexts where data shifts, device deprecation, and policy changes are common. To this end, we propose a bilevel optimization formulation of boundary-based unlearning that can be solved using iterative algorithms. We provide convergence guarantees when first order algorithms are used to unlearn and introduce a tunable loss design for controlling the forgetting–retention tradeoff. Across benchmark and real-world clinical imaging datasets, our approach outperforms baselines on both forgetting and retention metrics, including scenarios involving imaging devices and anatomical outliers. This work demonstrates the feasibility of unlearning on clinical imaging datasets and proposes it as a tool for model maintenance in scenarios that require removing the influence of specific data points without full model retraining.
Which OCT parameters can best predict visual field progression in glaucoma?
Authors: Abhishek Sethi, Homa Rashidisabet, Joelle A Hallak, Thasarat Sutabutr Vajaranant.
Primary open-angle glaucoma (POAG) is characterized by progressive loss of retinal ganglion cells (RGC), resulting in visual field (VF) loss. Although standard automated perimetry can assess visual function, 25 to 35% of RGC must be lost prior to significant VF abnormalities. Additionally, fixation losses, false positive, and false negative results on VF tests can cloud judgment of glaucoma severity. Thus, accurate measurement of RGC structural changes is critical to predict VF changes. Optical coherence tomography (OCT) provides non-invasive imaging to assess structural glaucomatous damage and can guide management in patients. The retinal nerve fiber layer (RNFL) consists of RGC axons, and peripapillary RNFL (pRNFL) thinning has been strongly associated with VF progression in patients (HR 8.44; 95% CI: 3.30–21.61) based on Early Manifest Glaucoma Trial criteria. However, drawbacks persist with RNFL measurements. For example, monitoring of advanced glaucoma may be limited by a floor effect, and high myopia can cause anatomical alterations such as peripapillary atrophy and optic nerve head tilt resulting in errors from OCT segmentation algorithms. Here, we will discuss the performance of macular OCT and neuroretinal rim width, in predicting VF changes in glaucoma patients when compared to RNFL thickness (RNFLT).
Tracking Surgeon- and Observer-Gaze as a Surrogate for Attention in Ophthalmic Surgery
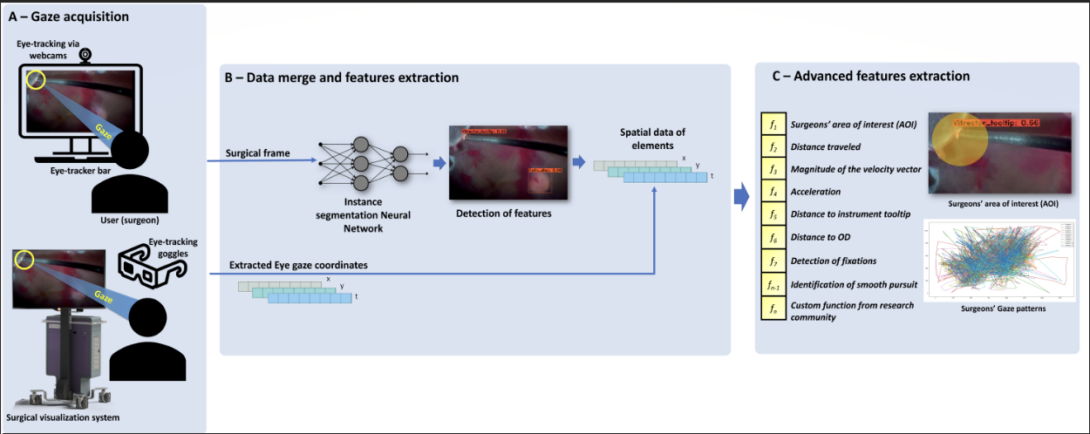
By: RG Nespolo, E Cole, D Wang, D Yi, Y Leiderman
Previous research identified disparities in eye movement between trainee and expert surgeons when watching surgery, improving surgical training for intraoperative decision–making. Although, no study of this kind was performed with ophthalmic surgeons. In this work, we developed and validated a platform that acquires the eye movement of ophthalmic surgeons when watching cataract and vitreoretinal procedures. Artificial Intelligence based tools obtained gaze patterns from the subjects, tracked prominent areas of visual attention such as instruments and retina elements, and performed post-hoc data analysis. Results revealed potential divergence in gaze patterns between attendings, fellows, and residents. In the near future, we hope these data can provide feedback to novice surgeons regarding the visual attention of experts during surgery.
Real-time instance segmentation during vitreoretinal microsurgery
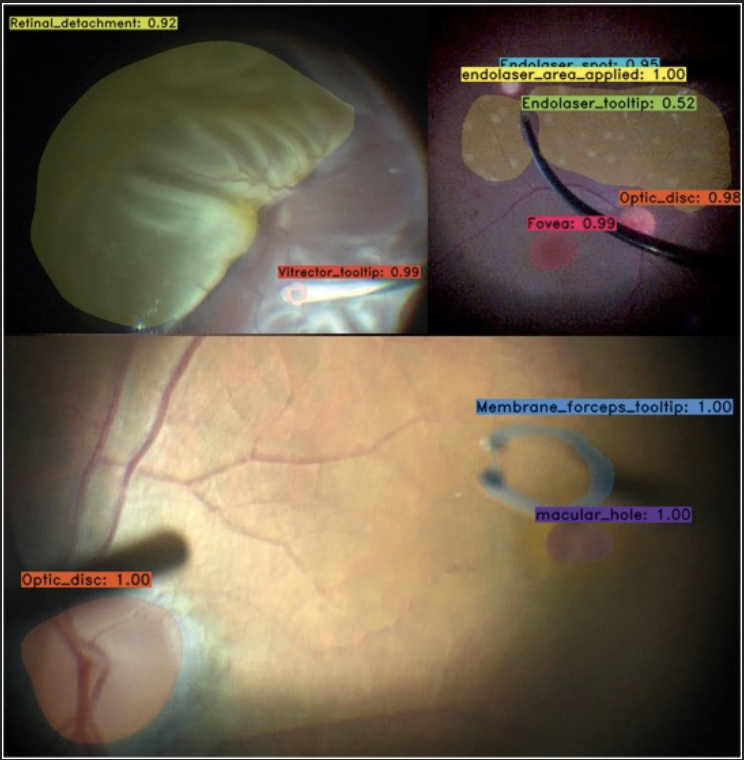
By: RG Nespolo, D Yi, E Cole, A Warren, D Wang, YI Leiderman
The application of AI-based image processing to ophthalmic microsurgery has the potential to improve performance, impact safety, and deepen our understanding of surgical training. The number of these solutions in ophthalmology has vastly increased during the last decade. Although, few solutions have been created with the potential to enhance ophthalmic microsurgery. Our study trained a deep learning neural network to detect, classify, and segment prominent features, such as instruments and tissues, during vitreoretinal microsurgery. The model was validated when integrated into a surgical microscope and visualization system. The results of this study will help researchers to develop and validate ideas using the spatial information pertaining to instruments and tissues, providing the basis for surgical guidance tools such as collision avoidance and semi-automated control of instrumentation parameters. Potential applications of the model also include the assessment of the progression in abilities of trainees via the analysis of instrumentation maneuvers.
Artificial Intelligence–Based Intraoperative Guidance Tools for Phacoemulsification Cataract Surgery
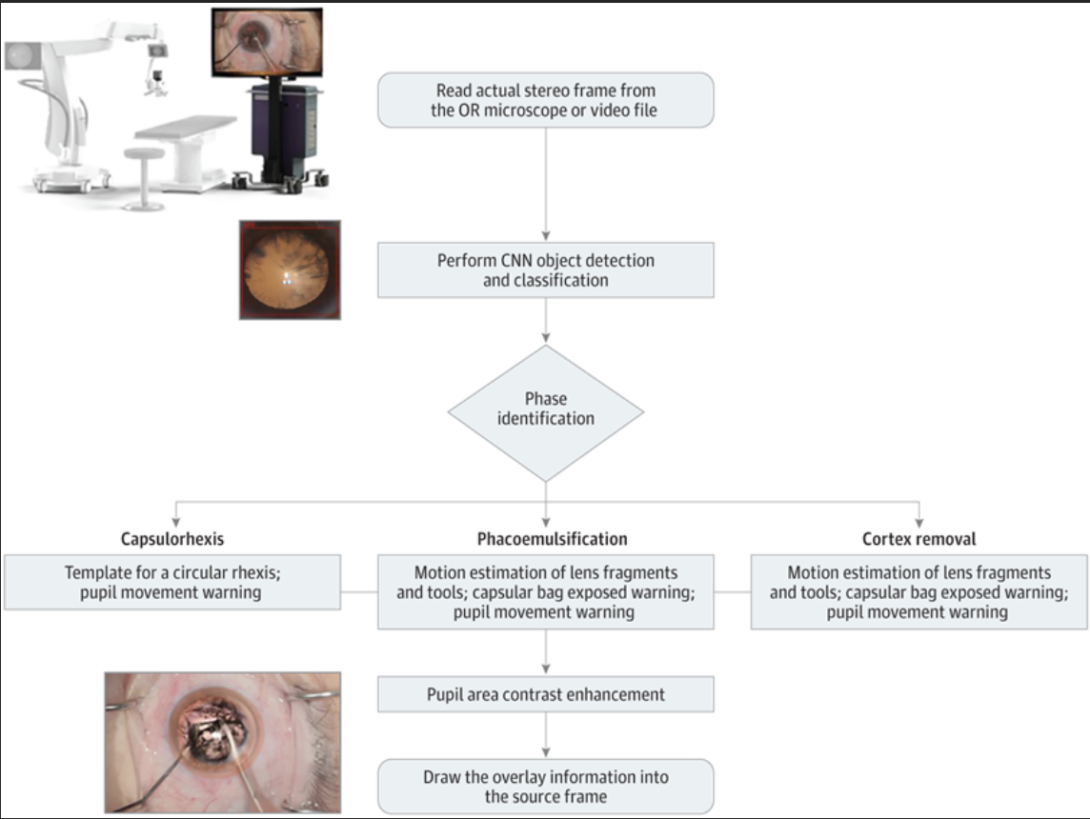
By: RG Nespolo, D Yi, E Cole, N Valikodath, C Luciano, YI Leiderman
Complications that arise from phacoemulsification procedures can lead to worse visual outcomes. Real-time image processing with artificial intelligence tools can extract data to deliver surgical guidance, potentially enhancing the surgical environment. In this study, a computer vision approach using deep neural networks was able to pupil track, identify the surgical phase being executed, and activate surgical guidance tools. These results suggest that an artificial intelligence–based surgical guidance platform has the potential to enhance the surgeon experience in phacoemulsification cataract surgery. Furthermore, this proof-of-concept investigation suggests that a pipeline from a surgical microscope could be integrated with neural networks and computer vision tools to provide surgical guidance in real time.
Auto-Ptosis
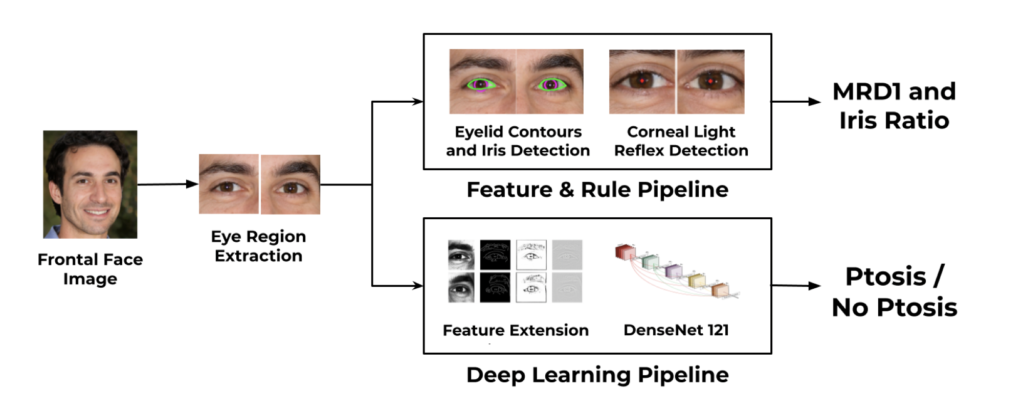
By: Abdullah Aleem, Manoj Prabhakar Nallabothula, Pete Setabutr, Joelle A. Hallak, and Darvin Yi
Blepharoptosis, or ptosis as it is more commonly referred to, is a condition of the eyelid where the upper eyelid droops. The current diagnosis for ptosis involves cumbersome manual measurements that are time-consuming and prone to human error. In this paper, we present AutoPtosis, an artificial intelligence based system with interpretable results for rapid diagnosis of ptosis. We utilize a diverse dataset collected from the Illinois Ophthalmic Database Atlas (I-ODA) to develop a robust deep learning model for prediction and also develop a clinically inspired model that calculates the marginal reflex distance and iris ratio. AutoPtosis achieved 95.5% accuracy on physician verified data that had an equal class balance. The proposed algorithm can help in the rapid and timely diagnosis of ptosis, significantly reduce the burden on the healthcare system, and save the patients and clinics valuable resources.
CvS: Classification via Segmentation For Small Datasets
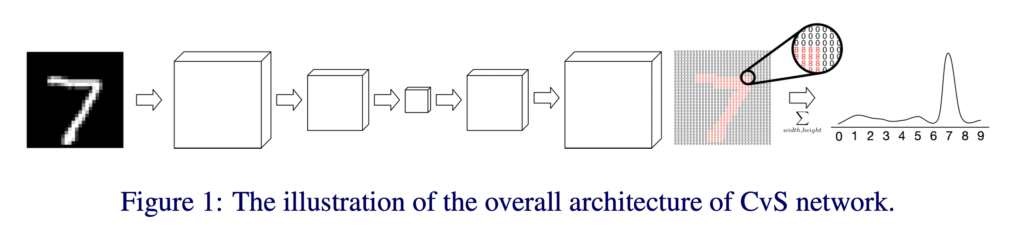
By: Nooshin Mojab, Philip S. Yu, Joelle A. Hallak, Darvin Yi
Deep learning models have shown promising results in a wide range of computer vision applications across various domains. The success of deep learning methods relies heavily on the availability of a large amount of data. Deep neural networks are prone to overfitting when data is scarce. This problem becomes even more severe for neural network with classification head with access to only a few data points. However, acquiring large-scale datasets is very challenging, laborious, or even infeasible in some domains. Hence, developing classifiers that are able to perform well in small data regimes is crucial for applications with limited data. This paper presents CvS, a cost-effective classifier for small datasets that derives the classification labels from predicting the segmentation maps. We employ the label propagation method to achieve a fully segmented dataset with only a handful of manually segmented data. We evaluate the effectiveness of our framework on diverse problems showing that CvS is able to achieve much higher classification results compared to previous methods when given only a handful of examples.
I-ODA, Real-World Multi-modal Longitudinal Data for OphthalmicApplications
By: Nooshin Mojab, Vahid Noroozi, Abdullah Aleem, Manoj P. Nallabothula, Joseph Baker, Dimitri T. Azar, Mark Rosenblatt, RV Paul Chan, Darvin Yi, Philip S. Yu, Joelle A. Hallak
Data from clinical real-world settings is characterized by variability in quality, machine-type, setting, and source. One of the primary goals of medical computer vision is to develop and validate artificial intelligence (AI) based algorithms on real-world data enabling clinical translations. However, despite the exponential growth in AI based applications in healthcare, specifically in ophthalmology, translations to clinical settings remain challenging. Limited access to adequate and diverse real-world data inhibits the development and validation of translatable algorithms. In this paper, we present a new multi-modal longitudinal ophthalmic imaging dataset, the Illinois Ophthalmic Database Atlas (I-ODA), with the goal of advancing state-of-the-art computer vision applications in ophthalmology, and improving upon the translatable capacity of AI based applications across different clinical settings. We present the infrastructure employed to collect, annotate, and anonymize images from multiple sources, demonstrating the complexity of real-world retrospective data and its limitations. I-ODA includes 12 imaging modalities with a total of 3,668,649 ophthalmic images of 33,876 individuals from the Department of Ophthalmology and Visual Sciences at the Illinois Eye and Ear Infirmary of the University of Illinois Chicago (UIC) over the course of 12 years.